📬 Melanoma Intelligence Digest — Week 2026-W44
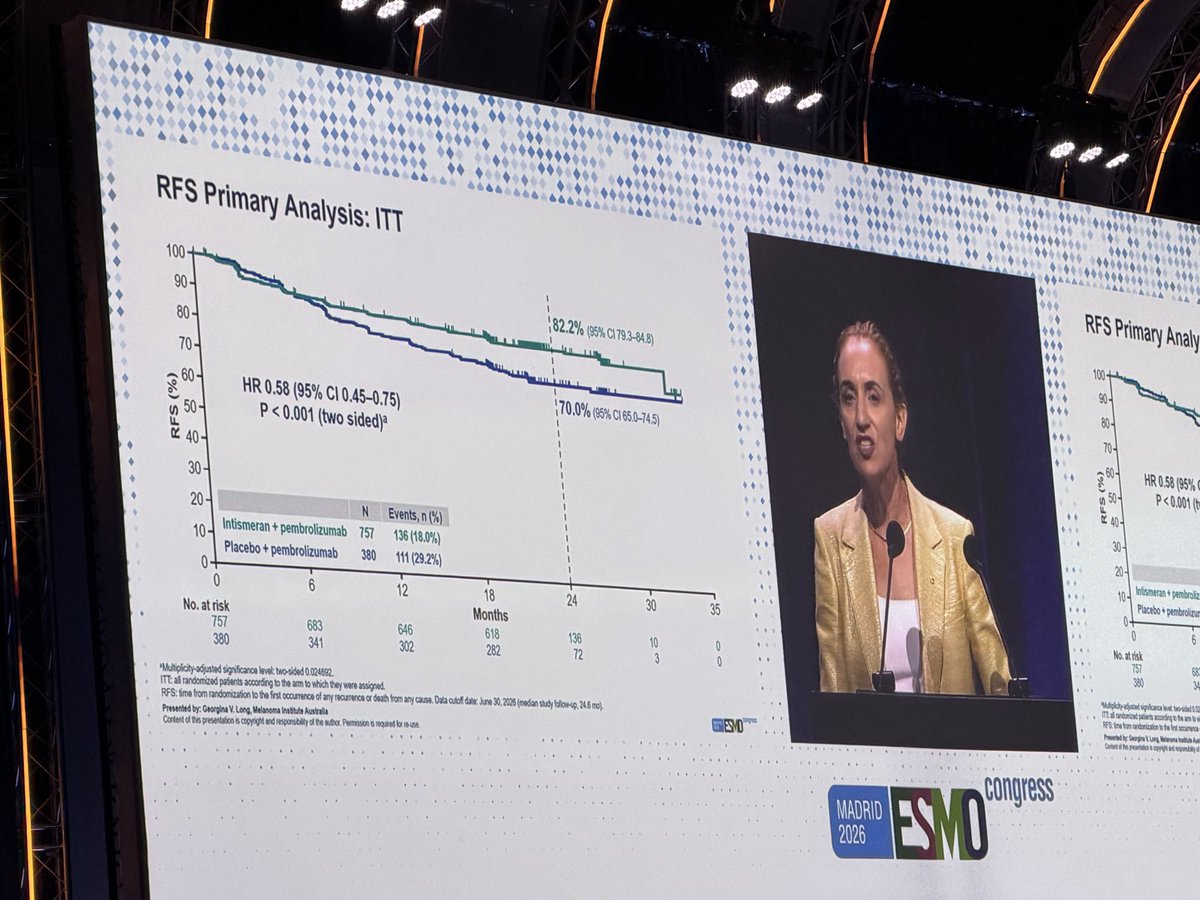
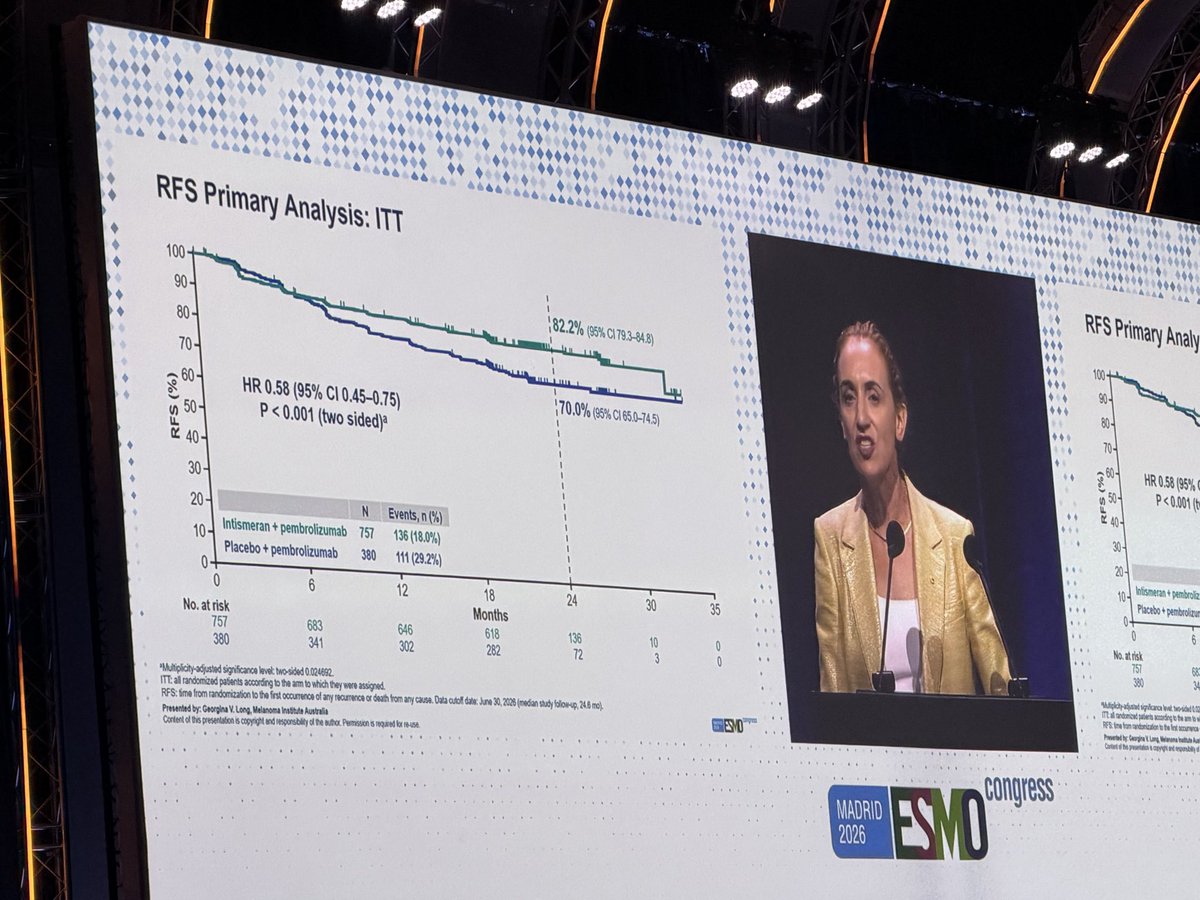
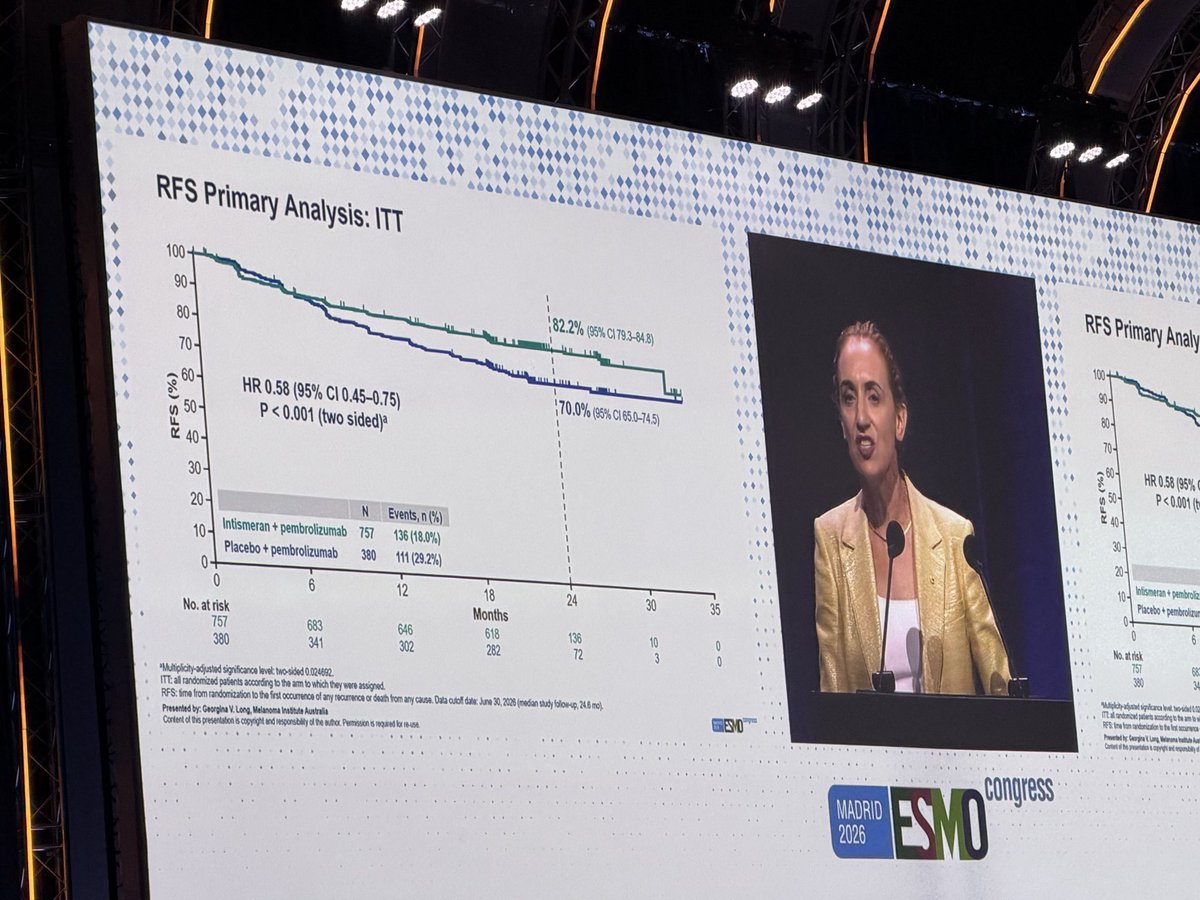
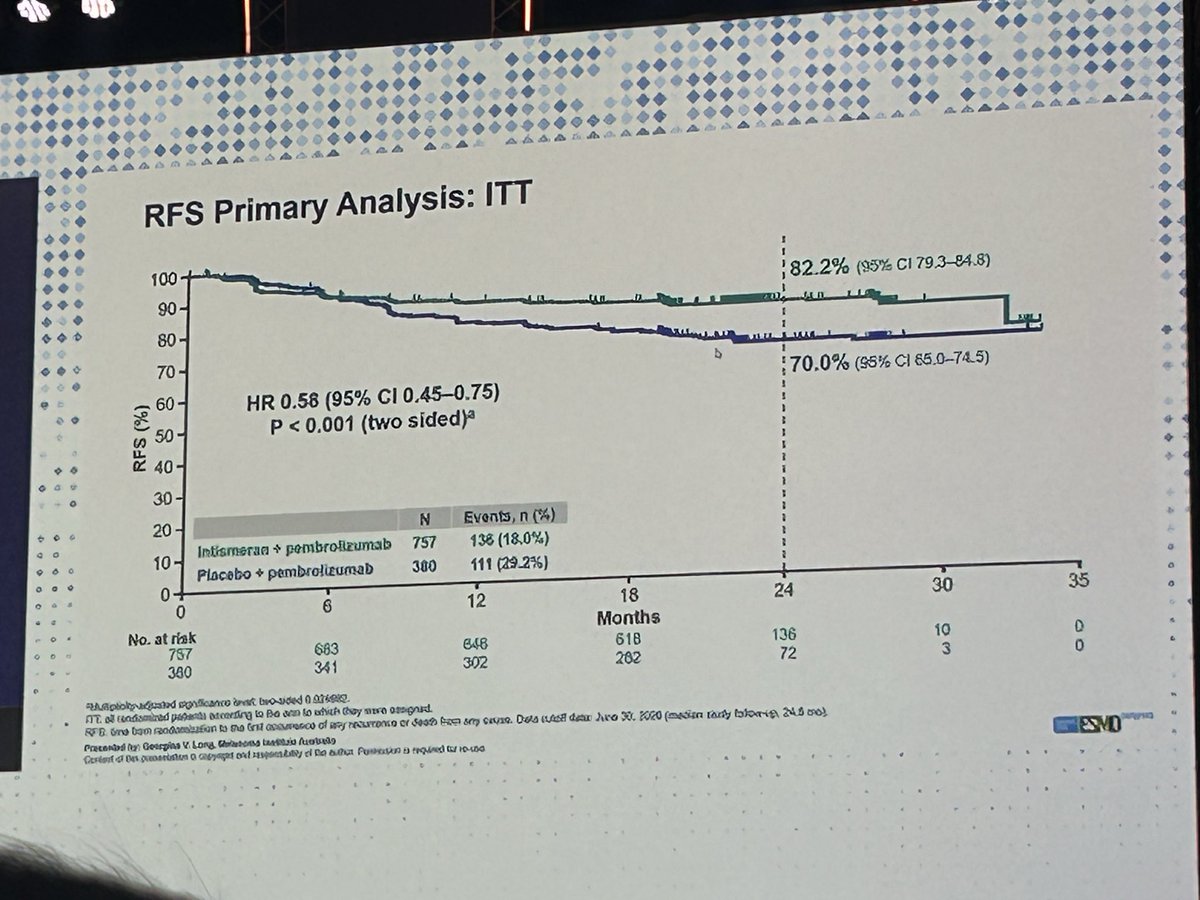
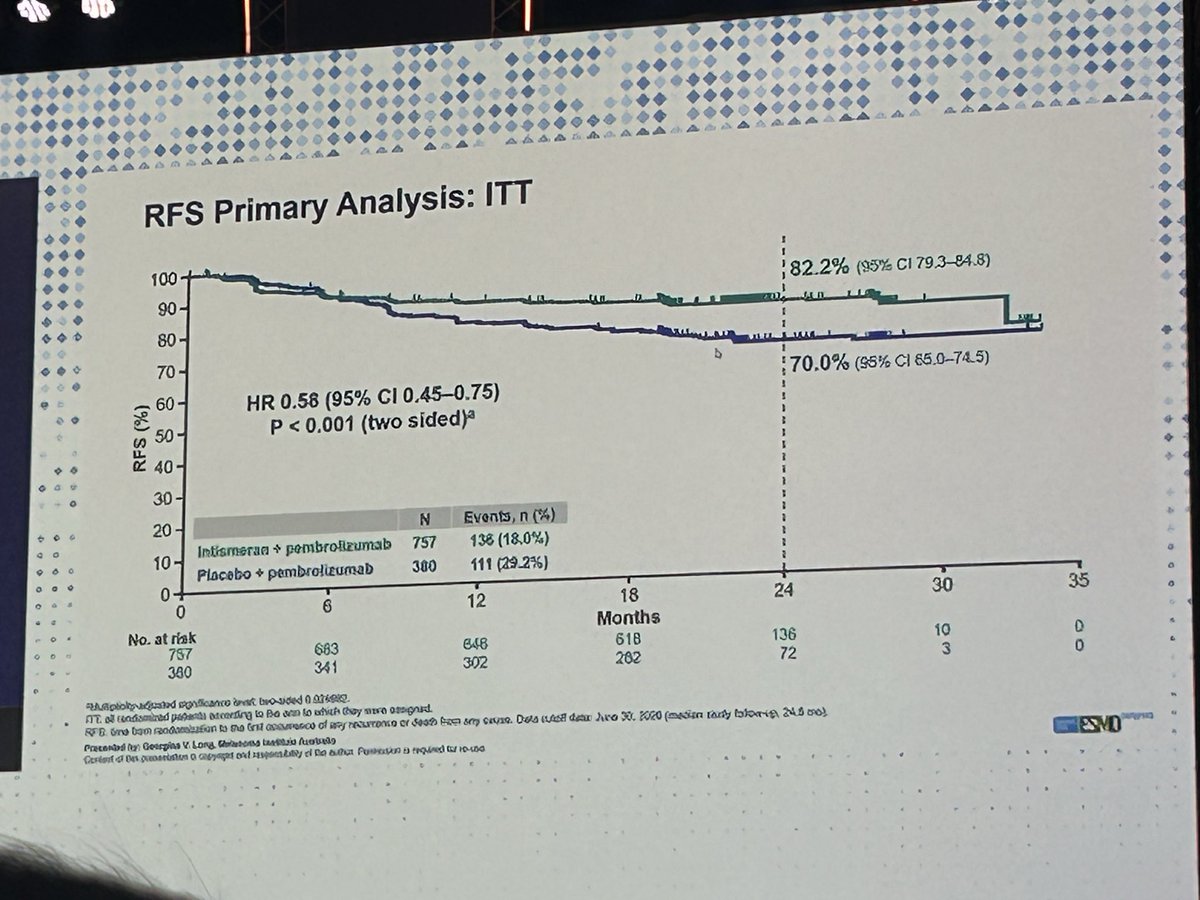
ESMO 2026 delivered the first positive phase 3 individualized neoantigen vaccine trial (INTerpath-001: 24-mo RFS 82.2% vs 70.0%, HR 0.58), alongside 5-year RELATIVITY-047 survival data, HBI-8000 PFS results, neoadjuvant cemiplimab final analysis in cSCC, and an NCCN listing for cosibelimab.
⚡ TL;DR
📄 Publications
- Relatlimab plus nivolumab versus nivolumab for advanced melanoma: 5-year survival and biomarker analyses of the phase 3 RELATIVITY-047 trial. — Phase 2-3 double-blind trial randomizing patients with metastatic/unresectable melanoma 1:1 to nivolumab 480 mg plus relatlimab 160 mg (n = 355) or nivolumab 480 mg (n = 359) every 4 weeks
🐦 Twitter / 🦋 Bluesky
- INTerpath-001: first positive phase 3 individualized mRNA neoantigen vaccine in resected melanoma, with RFS HR 0.58 and immature OS — Double-blind phase 3, n=1137 randomized 2:1 to intismeran + pembrolizumab vs placebo + pembrolizumab in resected stage IIB-IV melanoma, median follow-up 24.6 months
- RELATIVITY-047 five-year analysis: nivolumab plus relatlimab sustains OS and PFS benefit at minimum 57.3 months — In 714 patients with advanced melanoma, nivolumab plus relatlimab improved OS HR 0.78 (95% CI 0.64 to 0.95) and PFS HR 0.77 (95% CI 0.65 to 0.92) at minimum 57.3 months follow-up
- Access and cost of a per-patient manufactured vaccine become the second argument about INTerpath-001 — Clinicians flagged huge logistics and potential global oncology disparities for deployment of a personalized adjuvant mRNA vaccine
- Melanoma in pregnancy and transplant recipients: ESMO session confronts the patients trials exclude — Evidence in melanoma during pregnancy remains scarce, immune checkpoint inhibitors may disrupt fetal-maternal tolerance with prematurity/IUGR concern, and anti-LAG3 pregnancy data are essentially none
- IOV-COM-202 and MIZAR-003: TIL therapy moves into first line and tries to shed its toxicity burden — IOV-COM-202 cohort 1A, lifileucel plus pembrolizumab in first-line melanoma (n=24): ORR 62.5%, CR 29%, median PFS 19.8 months, median DOR not reached at 26.9 months follow-up
Full details below ↓
📄 What's Being Published
Relatlimab plus nivolumab versus nivolumab for advanced melanoma: 5-year survival and biomarker analyses of the phase 3 RELATIVITY-047 trial. — Long Georgina V et al., Nat Med
In this phase 2-3 double-blind trial, patients with metastatic/unresectable melanoma were randomized 1:1 to nivolumab 480 mg plus relatlimab 160 mg (n = 355) or nivolumab 480 mg (n = 359) every 4 weeks. At a minimum follow-up of 57.3 months, the doublet continued to show benefit over nivolumab for PFS (hazard ratio = 0.77; 95% confidence interval: 0.65-0.92), OS (hazard ratio = 0.78; 95% confidence interval: 0.64-0.95), and MSS (hazard ratio = 0.71; 95% confidence interval: 0.57-0.88), with a safety profile consistent with prior reports. Among biomarker-evaluable patients in the PD-L1 ≥1% subgroup, high peripheral or tumor LAG-3+ CD8 cell levels were associated with worse outcomes on nivolumab alone.
Clinical bottom line: Five-year data confirm a durable PFS, OS and melanoma-specific survival advantage for nivolumab plus relatlimab over nivolumab alone in advanced melanoma. This supports continued first-line use of the doublet and points to LAG-3+ CD8 levels as a candidate selection marker.
🗂 Every paper considered this week, including the ones that didn’t make it →
🗣️ What People Were Discussing This Week
How these are chosen: filtered for clinical relevance, grouped by the new development discussed, then ordered by engagement (bookmarks and reposts).
INTerpath-001: first positive phase 3 individualized mRNA neoantigen vaccine in resected melanoma, with RFS HR 0.58 and immature OS
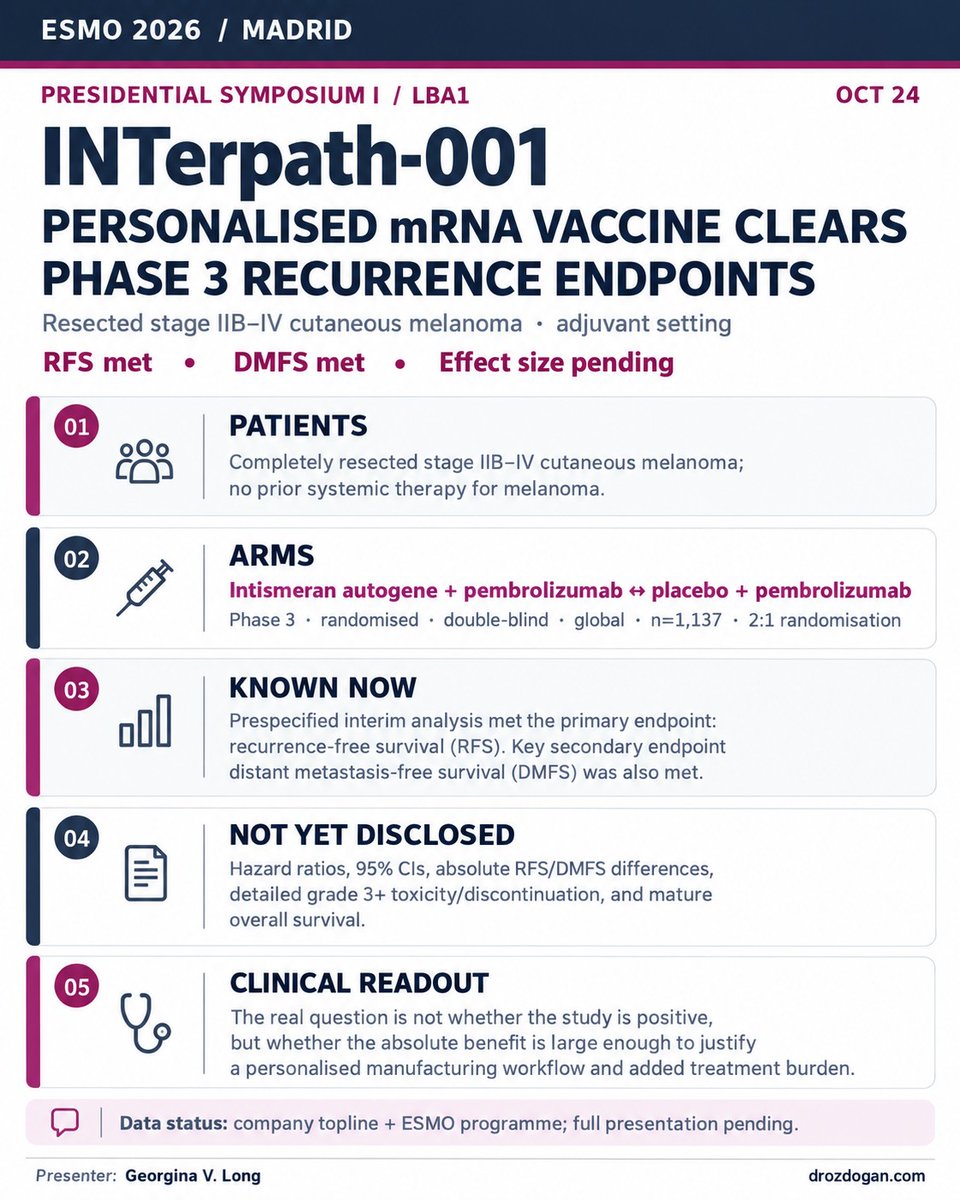
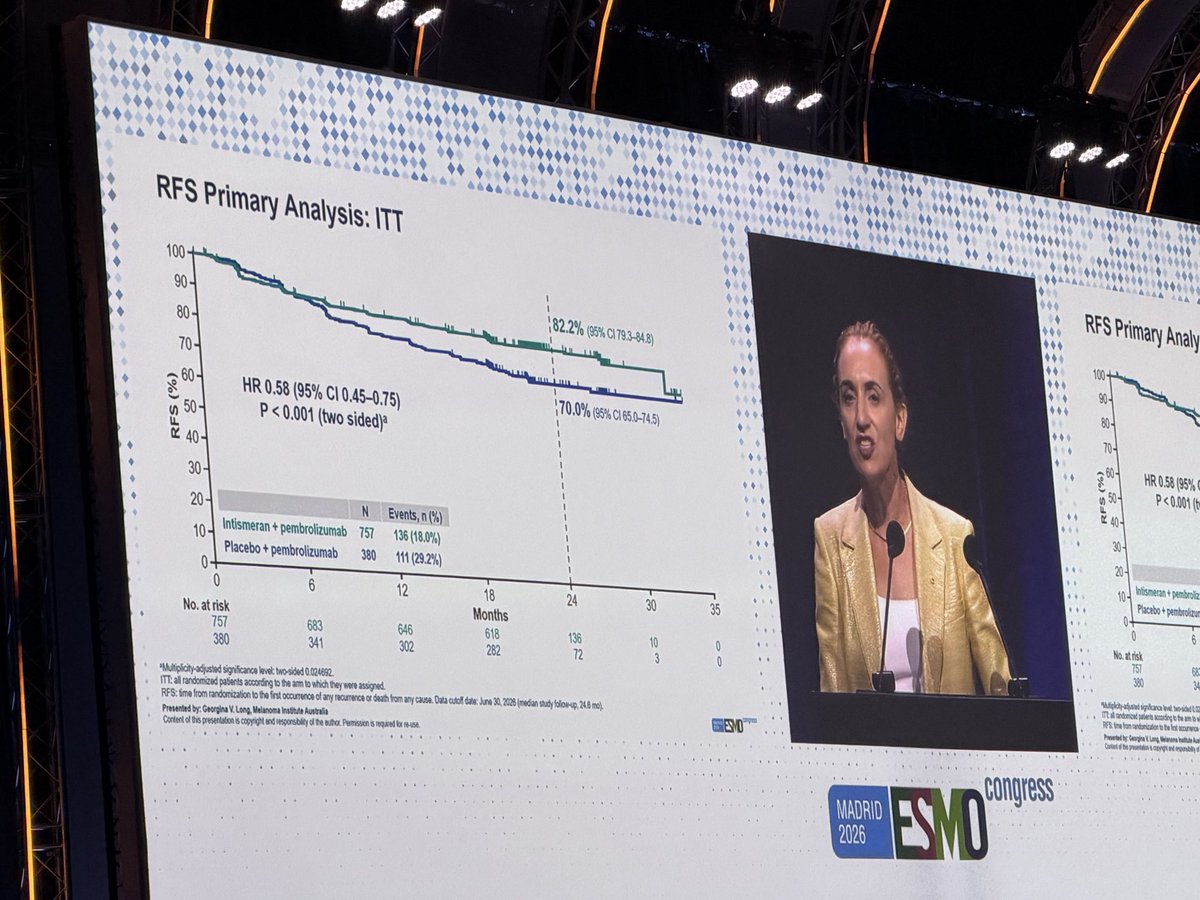
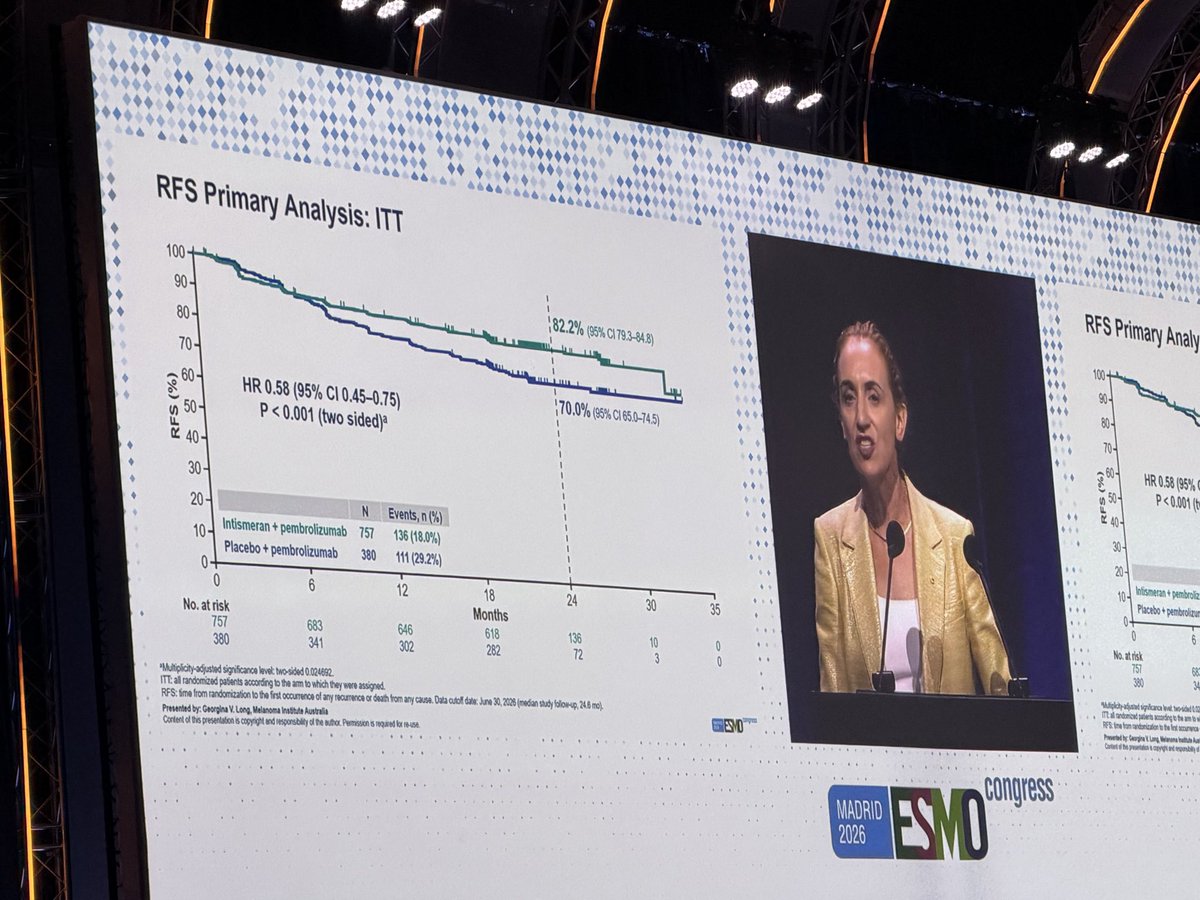
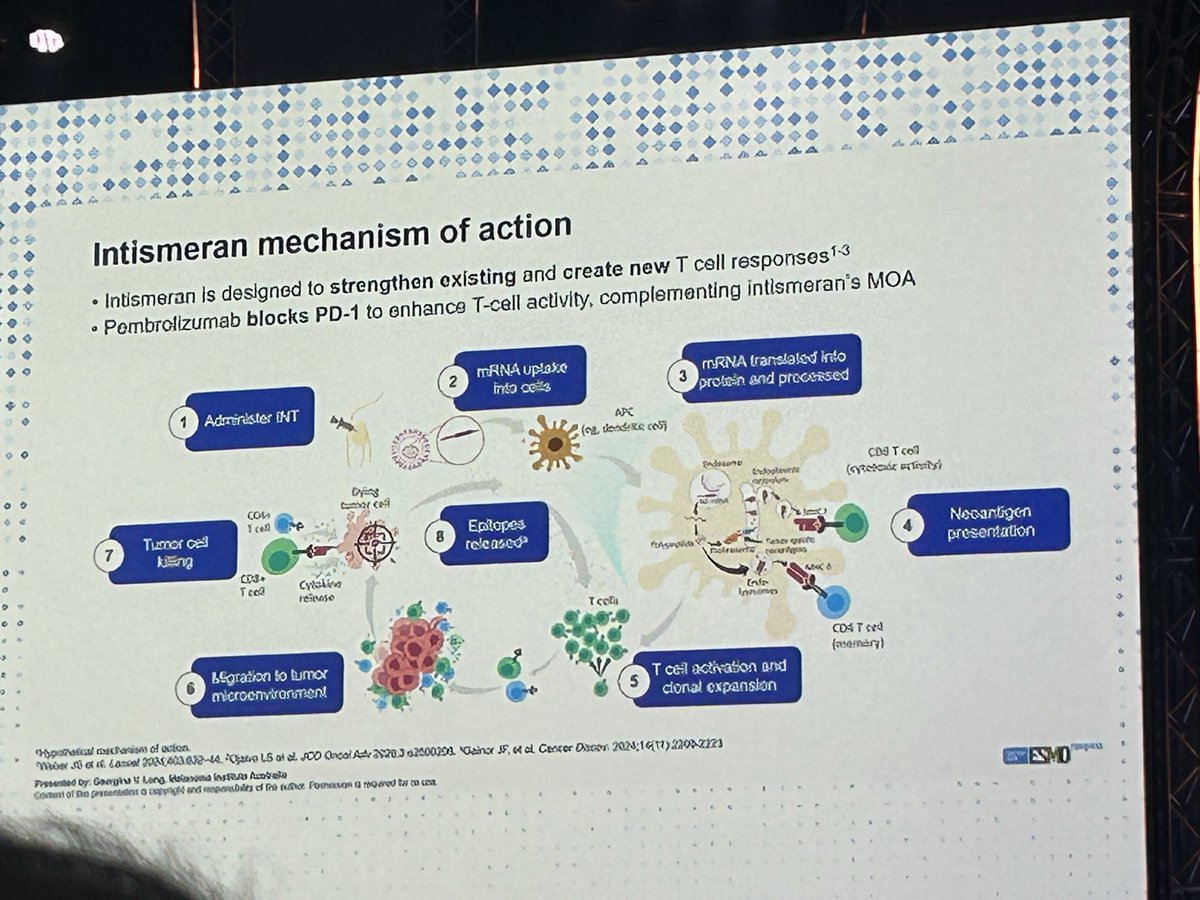
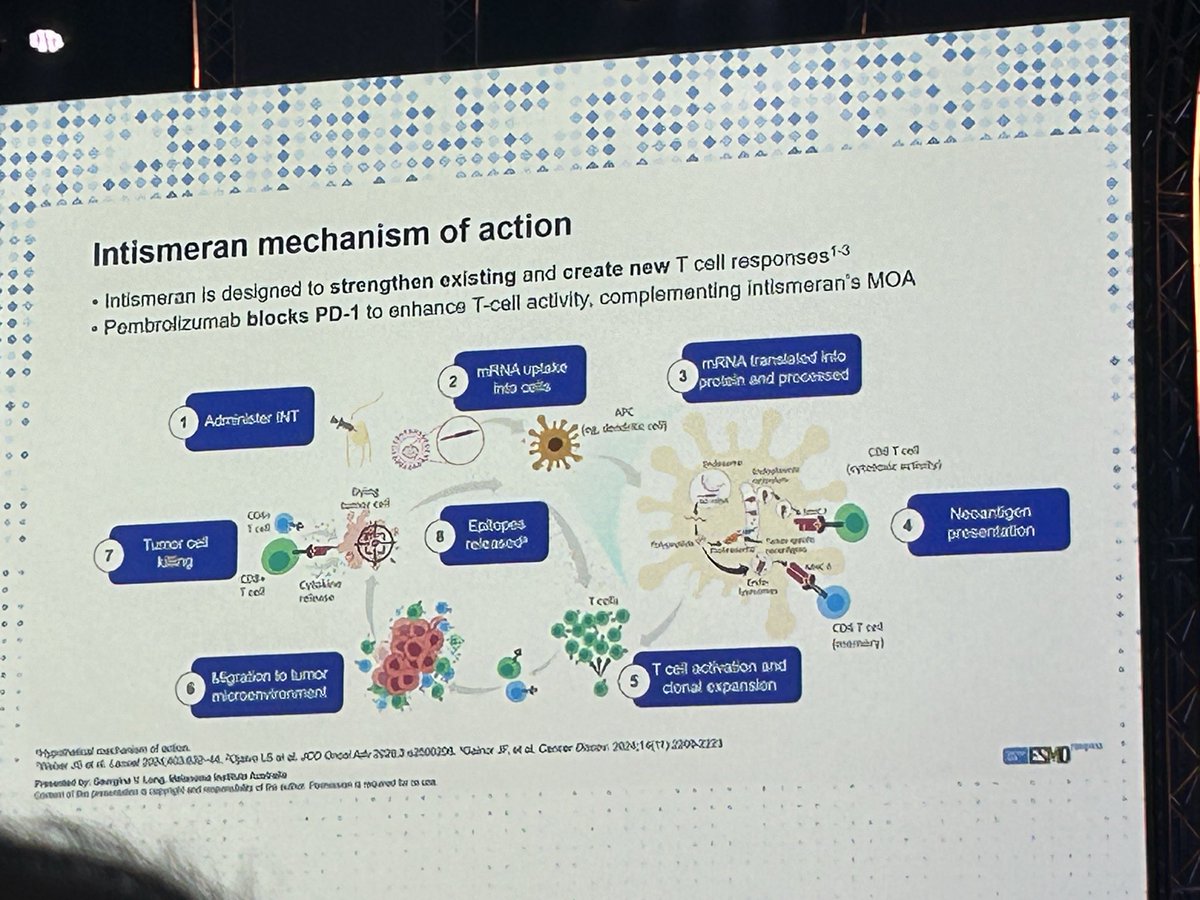
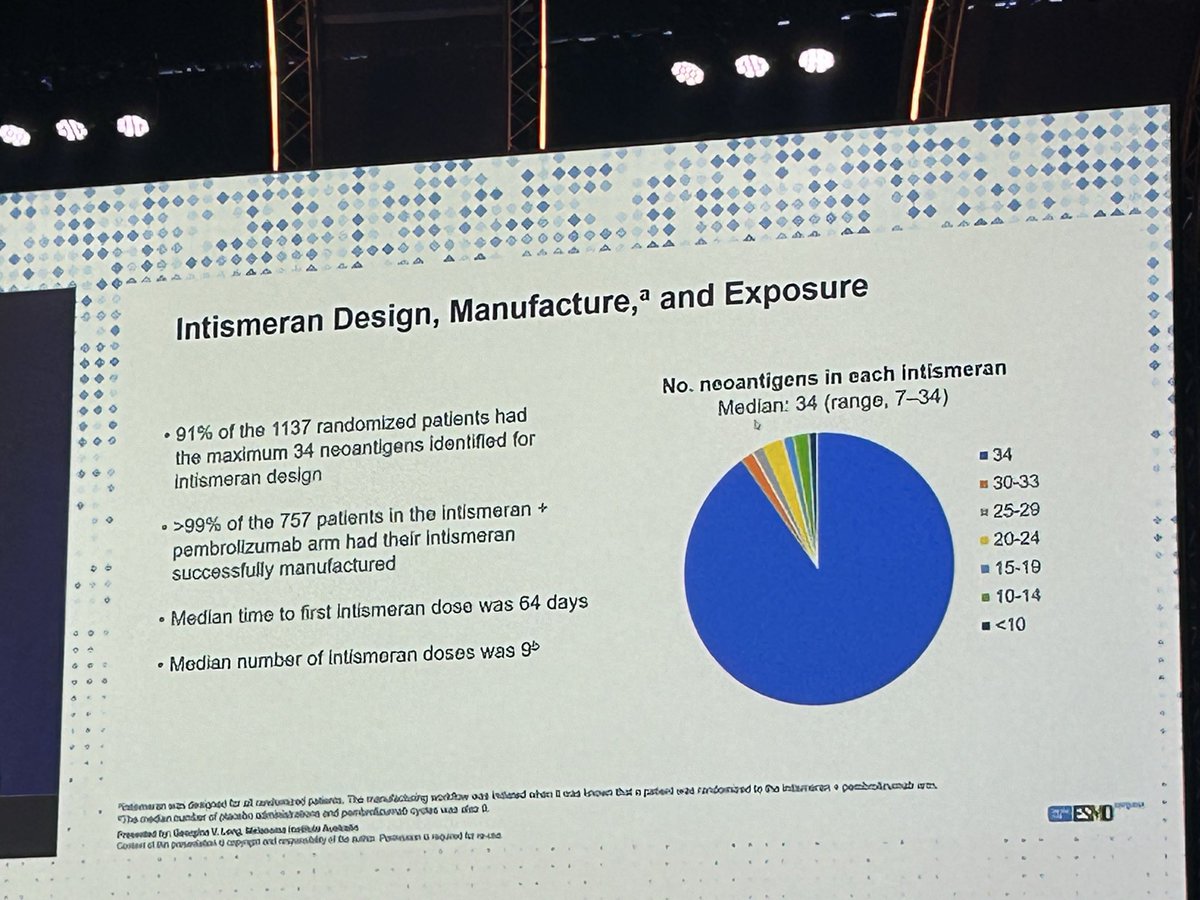
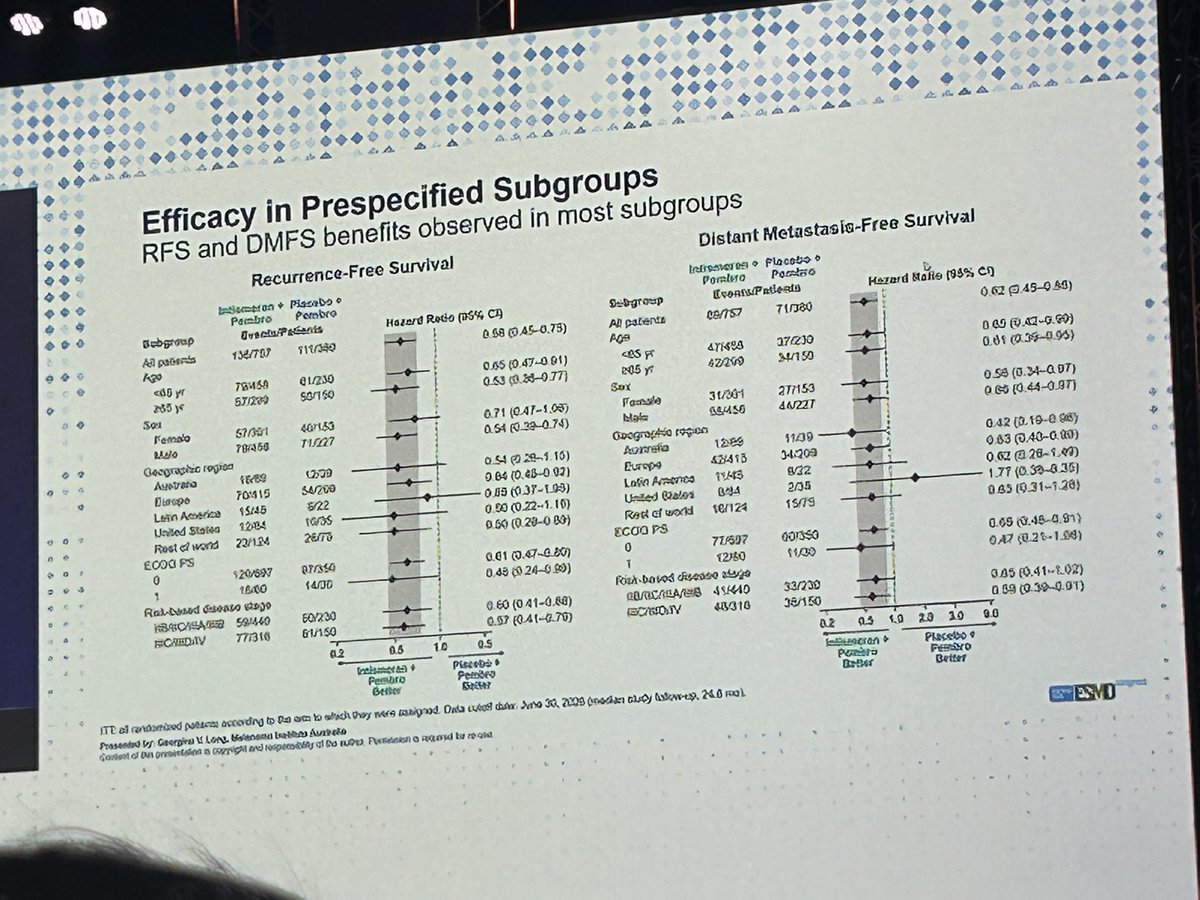
The double-blind phase 3 trial added intismeran to pembrolizumab as adjuvant therapy in resected stage IIB–IV melanoma. The vaccine arm improved both relapse-free and distant metastasis-free survival, but overall survival remains immature and not significant. Grade 5 events clustered in the experimental arm, although most were not considered treatment-related. Clinicians also cited a tissue screen-failure rate, a weeks-long manufacturing lag and the absence of a selection biomarker, against near-universal manufacturing success. ESMO lifted the LBA1 embargo after it was breached. The debate is about positioning: critics argue the trial does not establish added value over neoadjuvant immunotherapy in macroscopic stage III disease, while defenders point out that it also enrolled node-negative IIB/IIC and sentinel-node-positive patients who were never neoadjuvant candidates.
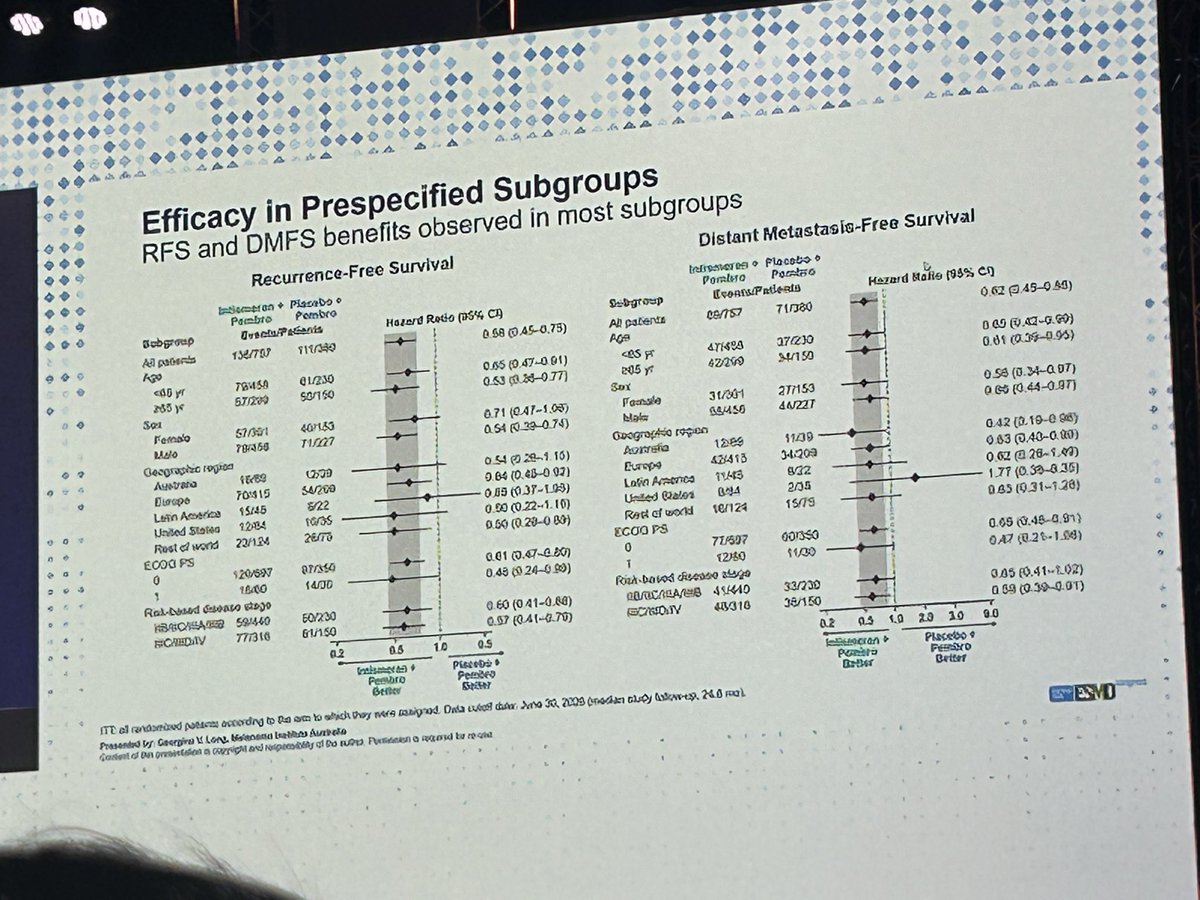
Key numbers: 24-mo RFS 82.2% vs 70.0%, HR 0.58 · 24-mo DMFS 88.5% vs 80.2%, HR 0.62 · OS HR 0.77, p=0.33 · Grade ≥3 AEs 23.6% vs 20.3% · Pyrexia 52.2% vs 8.2%
Discussed by: @GlopesMd, @FernandoOnco, @EricTopol, @LorenzaRimassa, @GIMedOnc, @dr_yakupergun, @LorenzaRimassa, @DrChoueiri, @GIMedOnc, @myESMO, @dr_yakupergun, @BalazsHalmosMD, @YGaritaonaindia, @FunchainMD, @FordePatrick, @YGaritaonaindia, @Latinamd, @FernandoOnco, @ozdogan_md, @katy_beckermann, @Melanoma_doctor, @OmidHamidMD
Sources cited: STAT News
RELATIVITY-047 five-year analysis: nivolumab plus relatlimab sustains OS and PFS benefit at minimum 57.3 months
At five years, clinicians highlighted sustained overall and progression-free survival benefit for nivolumab plus relatlimab versus nivolumab in advanced melanoma, along with a melanoma-specific survival advantage. The melanoma-specific survival and biomarker analyses were post-hoc or exploratory. High baseline LAG3hi CD8+ T cells were associated with improved response in the combination arm, while high LAG-3+ CD8 levels tracked with worse outcomes on nivolumab alone in the PD-L1 ≥1% subgroup. The open question is whether the doublet should be preferred for all comers or reserved for patients with high LAG-3+ CD8 levels.
Key numbers: OS HR 0.78 (95% CI 0.64 to 0.95) · PFS HR 0.77 (95% CI 0.65 to 0.92) · MSS HR 0.71 (0.57-0.88)
Discussed by: @cpgale3, @ilyassahinMD
Access and cost of a per-patient manufactured vaccine become the second argument about INTerpath-001
Clinicians flagged major logistics and potential global oncology disparities in deploying a personalized adjuvant mRNA vaccine designed from each patient's own tumour tissue. The discussant listed manufacturing complexity, treatment delays, costs and access as major challenges, alongside the open question of where adjuvant vaccination fits relative to neoadjuvant ipilimumab/nivolumab. The results now enter a regulatory review that may take several years. Clinicians also noted that the gap between press release and presentation meant months of counselling patients without the full data. The unresolved issue is which health systems can deliver a product requiring 6 to 8 weeks of per-patient manufacturing, and how to counsel patients who cannot access it.
Discussed by: @Latinamd, @NarjustFlorezMD, @GlopesMd
Melanoma in pregnancy and transplant recipients: ESMO session confronts the patients trials exclude
Jessica Borgers' ESMO session on melanoma and pregnancy noted that evidence remains scarce. Immune checkpoint inhibitors may disrupt fetal-maternal tolerance, raising concern for prematurity and IUGR, and anti-LAG3 pregnancy data are essentially absent. BRAF/MEK inhibitors should be considered only case by case. In transplant recipients, checkpoint inhibitors can work, but rejection occurs in roughly 1 in 3. The practical debate is timing: after high-risk adjuvant therapy, the session advised ideally waiting about 3 years before pregnancy, and left open whether a major pathological response after neoadjuvant immunotherapy justifies a shorter interval.
Discussed by: @Latinamd, @scocmem, @MarioBalsaMD, @JankovicK
Sources cited: OncoDaily
IOV-COM-202 and MIZAR-003: TIL therapy moves into first line and tries to shed its toxicity burden
In IOV-COM-202, lifileucel plus pembrolizumab produced high response and complete response rates in first-line melanoma, with median duration of response not reached. The phase 3 comparator is pembrolizumab monotherapy rather than ipi-nivo, and lifileucel's known toxicity limits generalizability. In the randomized phase II MIZAR-003 trial in anti-PD-1-resistant melanoma, enriched for acral and mucosal disease, the IL-2-free, reduced-intensity GC101 TIL plus sintilimab roughly doubled-plus median PFS and raised response rates over chemotherapy, and the benefit held in acral and mucosal subgroups. Critics note the trial was open-label, used chemotherapy as a soft comparator and still produced a short median PFS, which leaves open whether TIL can move earlier or stays in post-PD-1 salvage.
Key numbers: MIZAR-003 mPFS 4.4 vs 1.6 mo, HR 0.44 · ORR 44% vs 8% · Acral ORR 45% vs 8% · Mucosal ORR 50% vs 0% · G≥3 TRAEs 42% vs 31%
Discussed by: @YGaritaonaindia, @YGaritaonaindia, @GlopesMd
NADINA update reignites the question of omitting adjuvant therapy in near-complete pathological responders
One clinician's reading of the NADINA update is that adjuvant therapy can be omitted only after pCR, not after near-pCR. That clinician also urged turning assumptions drawn from small trials into confirmatory trials before acting on them. Others framed the next steps after establishing neoadjuvant over adjuvant immunotherapy as defining risk thresholds below pCR and finding biomarkers. They also noted that ipi/nivo, rather than single-agent pembrolizumab, is often used neoadjuvantly, and that differing populations and RFS versus EFS endpoints make cross-trial comparisons messy.
Discussed by: @ivanpantic1980, @DrBetofMDPhD, @Melanoma_doctor
Neoadjuvant cemiplimab final analysis in stage II-IV cSCC published in JCO with 51% pCR and 54-month EFS 76.2%
The final analysis of the single-arm phase II R2810-ONC-1901 trial of neoadjuvant cemiplimab followed by surgery in resectable cSCC showed that about half of patients achieved a pathologic complete response. Long-term event-free and overall survival remained excellent. Because postoperative radiotherapy, cemiplimab or observation was left to investigator choice, the trial cannot establish that radiotherapy can be safely omitted. @DrNeilGross discussed what a future trial would need to show before complete responders could skip surgery.
Key numbers: pCR 51% · 54-mo EFS 76.2% · OS 79.4%
Discussed by: @DrNeilGross, @jryckman3, @VJOncology
Sources cited: Phase II Study of Neoadjuvant Cemiplimab for Stage II to IV Cutaneous Squamous Cell Carci… (Journal of Clinical Oncology, 2026)
IMA203CD8 PRAME-directed TCR-T reports phase 1 activity in melanoma with high rates of cytokine release syndrome
In this phase I trial in heavily pretreated HLA-A*02:01+, PRAME+ solid tumors, activity was concentrated in melanoma, synovial sarcoma, ovarian and uterine cancers, with some responses ongoing beyond 2.5 years. Cytokine release syndrome was nearly universal, though mostly low grade, and ICANS also occurred. Clinicians are weighing whether the melanoma response rate justifies that toxicity, and which post-PD-1 patients should go to TCR-T rather than TIL.
Key numbers: ORR 51%, cORR 41% · Melanoma ORR 52% · Synovial sarcoma ORR 67% · CRS 97% (G3: 8%, G4: 1%) · ICANS 8%
Discussed by: @OncoAlert, @DrMirallas
HBI-8000-303 phase 3: HBI-8000 plus nivolumab improves PFS in advanced melanoma but with a steep grade 3/4 toxicity cost
In the phase 3 HBI-8000-303 study in unresectable advanced melanoma, adding HBI-8000 to nivolumab significantly improved median PFS. The response rate gain did not reach significance. Grade 3/4 treatment-related toxicity rose sharply, and there were 4 treatment-related deaths on HBI-8000. The debate is whether this PFS gain justifies roughly tripled severe toxicity and four treatment-related deaths while OS is not yet reported.
Key numbers: mPFS 11.7 vs 7.4 mo, HR 0.73 · ORR 41.4% vs 32.3% (p=0.0569) · G3/4 TRAEs 54.8% vs 17.9%
Discussed by: @OncoAlert, @OncLive, @cancertherapyadv.bsky.social
Darovasertib plus crizotinib update in uveal melanoma, with neoadjuvant tumor shrinkage in 85.7%
Updated OptimUM findings support darovasertib plus crizotinib in uveal melanoma, with neoadjuvant darovasertib shrinking tumors in 85.7% of patients. Separately, phase 1 data showed preliminary antitumor activity for the PI3Kδ inhibitor roginolisib, including in metastatic uveal melanoma. The open question is whether neoadjuvant darovasertib should now be offered to patients facing enucleation, given that there is no randomized eye-preservation endpoint.
Discussed by: @cancertherapyadv.bsky.social, @OncLive
Sources cited: OncLive
NCCN adds cosibelimab as a category 2A preferred option for locally advanced cSCC
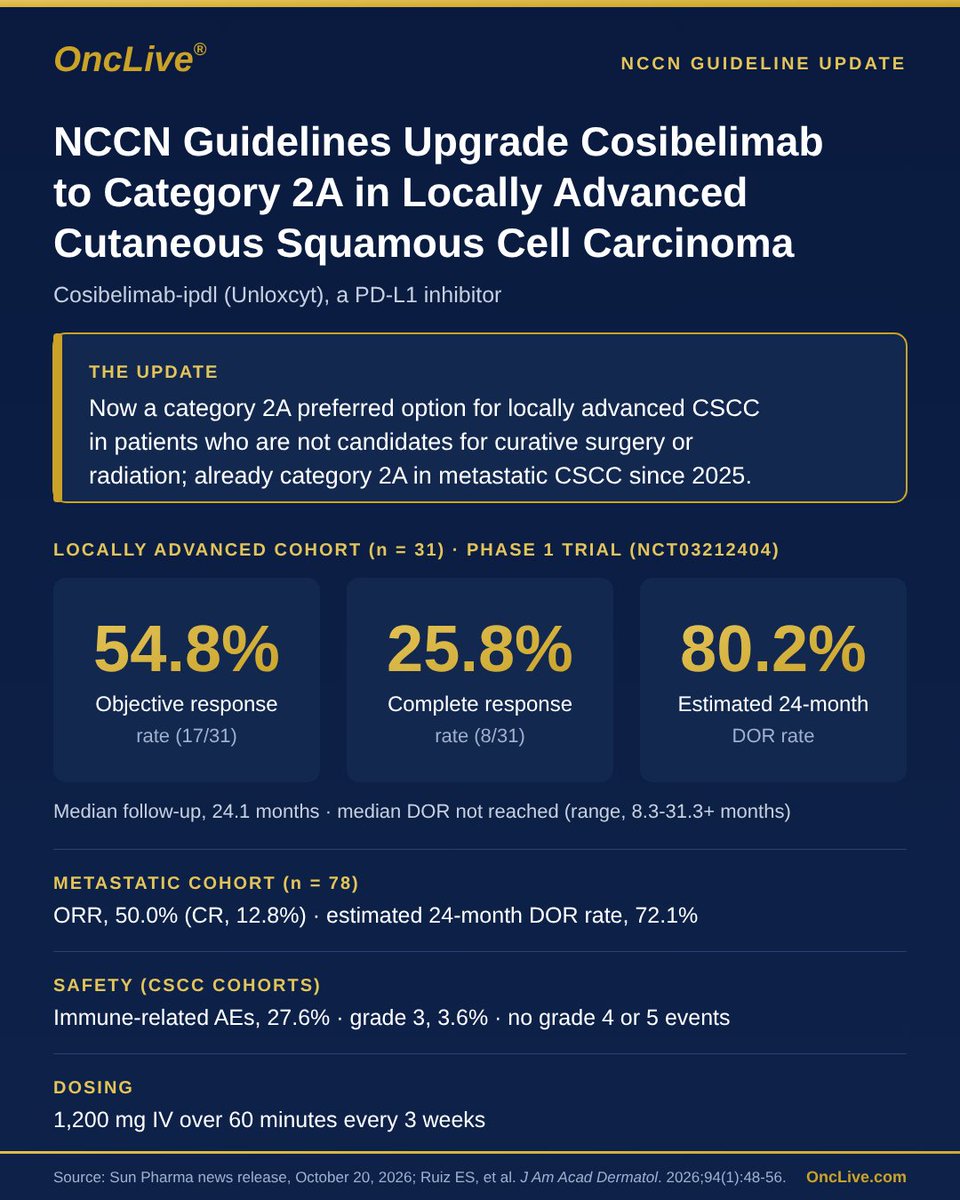
Updated NCCN guidelines now list cosibelimab (Unloxcyt) as a category 2A preferred option for locally advanced cutaneous squamous cell carcinoma in patients who are not candidates for curative surgery or radiation. The listing follows durable responses in the CK-301-101 trial. The practical question is how to choose or sequence cosibelimab against cemiplimab and pembrolizumab in this population.
Discussed by: @OncLive, @TargetedOnc, @DermTimesNow
Sources cited: OncLive · Targeted Oncology
🔥 Top Ranked Tweets
sciqst @sciqst
mRNA is no longer just a pandemic technology. 🚀
In 2026, Moderna and Merck reported a 49% reduction in melanoma recurrence or death risk over five years with personalized mRNA therapy [1].
A Phase 3 trial also met key endpoints [2]. This could reshape cancer treatment.
Meanwhile, mRNA-based RSV vaccines are expanding protection to more adults [3]. 🧬
The opportunity is huge. But manufacturing costs, regulatory complexity and unequal access remain barriers.
For biotech leaders, the next competitive edge is scalable, affordable production.
🤔 Should governments prioritize rapid mRNA innovation or equitable access and who should pay for both?
[1] [https://t.co/JiDh0JXE4J](https://t.co/Em4SydPoC7)
[2] [https://t.co/oJpjz8Z5YH](https://t.co/HuWz4IBG6F)
[3] [https://t.co/po2FTjL651](https://t.co/PIuGFNVjPX)
#mRNA #CancerVaccines #Biotech #VaccineInnovation
🔖 0 ❤️ 3 🔁 3 👁 171
Mustafa Özdoğan, MD @ozdogan_md
Personalised mRNA therapy reaches Phase 3 in melanoma: INTerpath-001 met RFS and DMFS with intismeran autogene + pembrolizumab. The key question now is magnitude-HRs, absolute benefit and detailed toxicity are still awaited.
Presented by @ProfGLongMIA at @myESMO.
Developed by @moderna_tx + @Merck.
#ESMO26 #Melanoma
🔖 0 ❤️ 5 🔁 4 👁 284
OncLive.com @OncLive
Updated @NCCN guidelines now include cosibelimab as a category 2A preferred option for patients with locally advanced cutaneous squamous cell carcinoma who are not candidates for curative surgery or radiation #oncology
Read more: https://t.co/9OuQaEBdHE https://t.co/J7jb6yEk2B
🔖 1 ❤️ 2 🔁 1 👁 815
Yago Garitaonaindía @YGaritaonaindia
🚨 #ESMO26 INTerpath-001 leaked before the embargo, so @myESMO released it early
➡️ Intismeran (mRNA-4157) + pembro vs placebo + pembro, adjuvant stage IIB-IV #melanoma
• 24-mo RFS 82.2% vs 70.0% | HR 0.58
• 24-mo DMFS 88.5% vs 80.2% | HR 0.62
• G≥3 AEs 23.6% vs 20.3%
👇👇
🔖 3 ❤️ 7 🔁 1 👁 1,411
Morning Glory Sciences @MorningGlorySci
Merck and Moderna released detailed Phase 3 INTerpath-001 data for intismeran + pembrolizumab in resected melanoma ahead of ESMO LBA1. What the numbers show, and what is still not disclosed:
#Melanoma #CancerVaccine
https://t.co/dPlvZGXq2c
🔖 0 ❤️ 0 🔁 0 👁 39
Merck @Merck
We announced positive Phase 3 data for our investigational individualized neoantigen therapy in combination with our company’s immunotherapy for patients with completely resected stage IIB-IV #melanoma in collaboration with @moderna_tx. Read more: https://t.co/jhETUTD2iO https://t.co/QOgrF8nhhi
🔖 0 ❤️ 11 🔁 0 👁 1,354
Targeted Oncology @TargetedOnc
🩺 Practice Update: The @NCCN guidelines have incorporated cosibelimab (Unloxcyt) for locally advanced cutaneous squamous cell carcinoma after favorable results in the CK-301-101 trial.
Read more: https://t.co/GQDOe2ps7c
#CSCC #SkinCancer #Oncology #CancerCare
🔖 0 ❤️ 5 🔁 0 👁 616
Dermatology Times @DermTimesNow
🚨 NEW TODAY: Cosibelimab-ipdl has received an NCCN Category 2A recommendation for patients with locally advanced cutaneous squamous cell carcinoma who are not candidates for curative surgery or radiation.
https://t.co/h0QpnUpn6Q
#Cosibelimab #cSCC #SkinCancer #Dermatology
🔖 0 ❤️ 1 🔁 0 👁 146
Elad Sharon @EladSharonMD
RT @DrChoueiri: Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
🔖 5 ❤️ 62 🔁 23 👁 4,146

Yago Garitaonaindía @YGaritaonaindia
RT @DrChoueiri: Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
🔖 5 ❤️ 62 🔁 23 👁 4,146

Gil Morgan, MD @weoncologists
RT @DrChoueiri: Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
🔖 5 ❤️ 62 🔁 23 👁 4,146

OncoAlert @OncoAlert
RT @DrChoueiri: Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
🔖 5 ❤️ 62 🔁 23 👁 4,146

Toni Choueiri, MD @DrChoueiri
Superb presentation by Georgina Long! INTerpath-001: adding personalized mRNA vaccine intismeran to pembrolizumab reduced recurrence/death risk by 42% in resected stage IIB-IV melanoma (HR 0.58). A major step for cancer vaccines! #ESMO26 @OncoAlert @myESMO #ESMO26 https://t.co/9miRzK7fhb
🔖 5 ❤️ 62 🔁 23 👁 4,146

Petros Grivas @PGrivasMDPhD
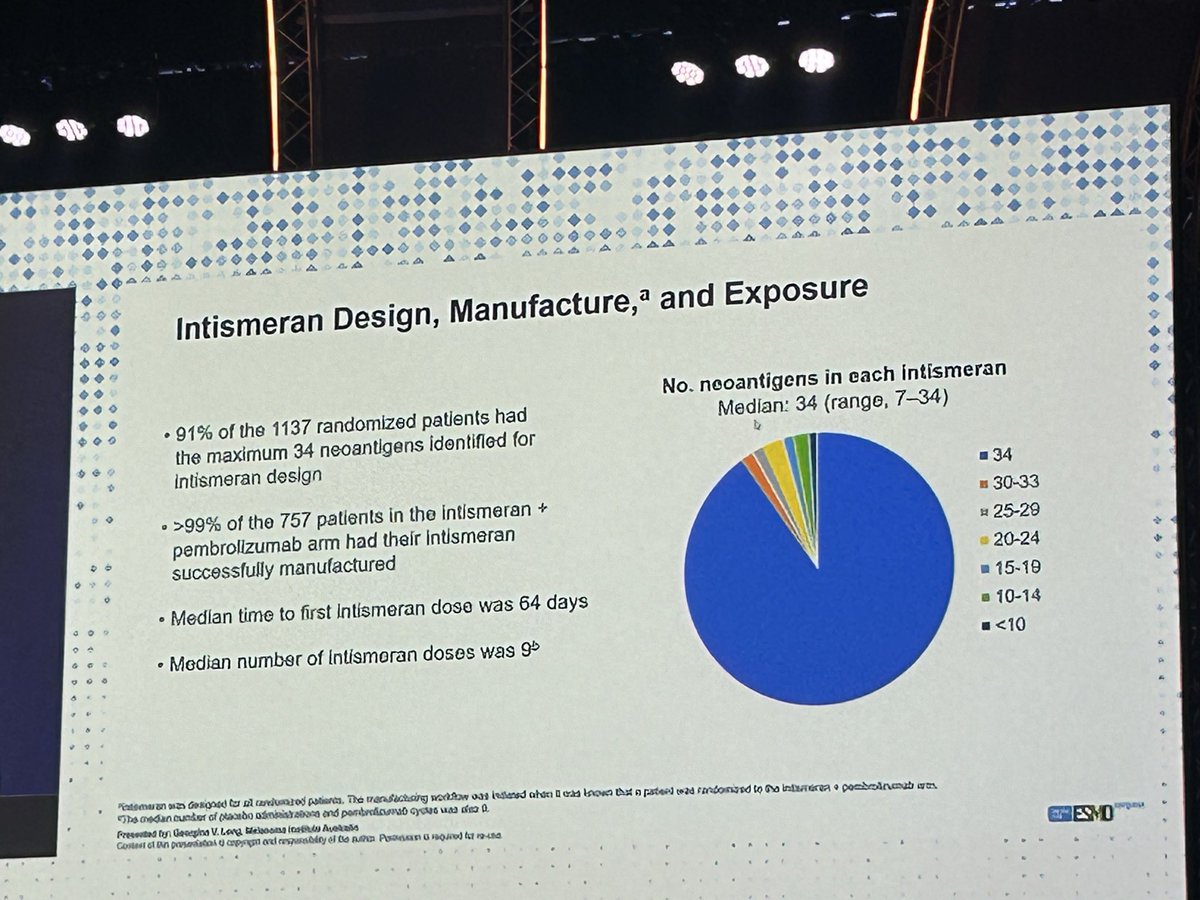
RT @YGaritaonaindia: 🔥 #ESMO26 INTerpath-001, full data (now yes)
On top of RFS HR 0.58 and DMFS HR 0.62:
• Manufacturing success >99%
• >90% of patients got the maximum 34 neoantigens
🔍 Practice-changing? For a population, yes. Two things still to prove:
• Can an mRNA strategy rescue patients primary refractory to neoadjuvant ipi-nivo (no pathologic response)?
• Will it move OS in stage II-IIIB too?
Resuls in @NEJM soon
@myESMO @OncoAlert @Larvol @_SEOM
#Melanoma #Immunotherapy
🔖 8 ❤️ 21 🔁 11 👁 5,145
gilberto lopes @GlopesMd
RT @YGaritaonaindia: 🔥 #ESMO26 INTerpath-001, full data (now yes)
On top of RFS HR 0.58 and DMFS HR 0.62:
• Manufacturing success >99%
• >90% of patients got the maximum 34 neoantigens
🔍 Practice-changing? For a population, yes. Two things still to prove:
• Can an mRNA strategy rescue patients primary refractory to neoadjuvant ipi-nivo (no pathologic response)?
• Will it move OS in stage II-IIIB too?
Resuls in @NEJM soon
@myESMO @OncoAlert @Larvol @_SEOM
#Melanoma #Immunotherapy
🔖 8 ❤️ 21 🔁 11 👁 5,145
🧪 Newly Recruiting Trials
1 trial (1 phase II) opened this week, testing axelopran
Phase 1/2 · John Kirkwood · axelopran · Pennsylvania · CT.gov ↗
Agent descriptions from the NCI Thesaurus.
Prepared by Rafael Santana-Davila, M.D. Questions or feedback? Just reply to this email.
Disclaimer: This digest is AI-generated. Content may contain errors -- always verify with original sources.
Know a colleague who would find this useful? Just forward them this email.
☕ Not funded by anyone — no sponsors, no pharma. Buy me a coffee if it's useful.